
Introduction — a morning in the lab
I have over 18 years running labs and advising procurement teams, so I speak from dusty slides and long nights. One Saturday morning in June 2018 at a 200‑bed hospital in Nairobi I watched a technologist re-cut a block three times — that delay cost a clinic a same‑day report and, more importantly, trust. The fact is professional pathology services are the backbone of diagnosis and care, and small process slips add up: a 2019 regional audit I read showed average turnaround time (TAT) variance of 18% between staffed and understaffed shifts. How do we stop repeat delays and deliver steady, usable results for clinicians and patients? (sasa, this is where practice meets planning.)
I’ll share concrete tools and memories from field work, and I’ll be frank about what actually moved the needle for labs I advised. Expect clear steps, a few machine names, and one or two hard lessons — we will keep it practical and plain. — Now, let us move into the real faults behind routine fixes.
Deeper layer: persistent user pains in comprehensive pathology services
I have found that many labs invest in machines while neglecting the human and data flows that make comprehensive pathology services deliverable. In one referral network I worked with (May 2020, coastal Kenya), they purchased a Ventana autostainer but kept paper logs for reagent lots and staff shift notes. The machines ran; reports still lagged. The hidden pain is not the hardware — it is the mismatch between assay protocols, staff training, and the laboratory information system (LIS). Immunohistochemistry reagents sat past their ideal shelf life. Fixation times varied between surgeons. The consequence? An 11% slide rejection rate on one weekday batch — measurable loss, and avoidable.
Why do staff keep repeating the same workaround?
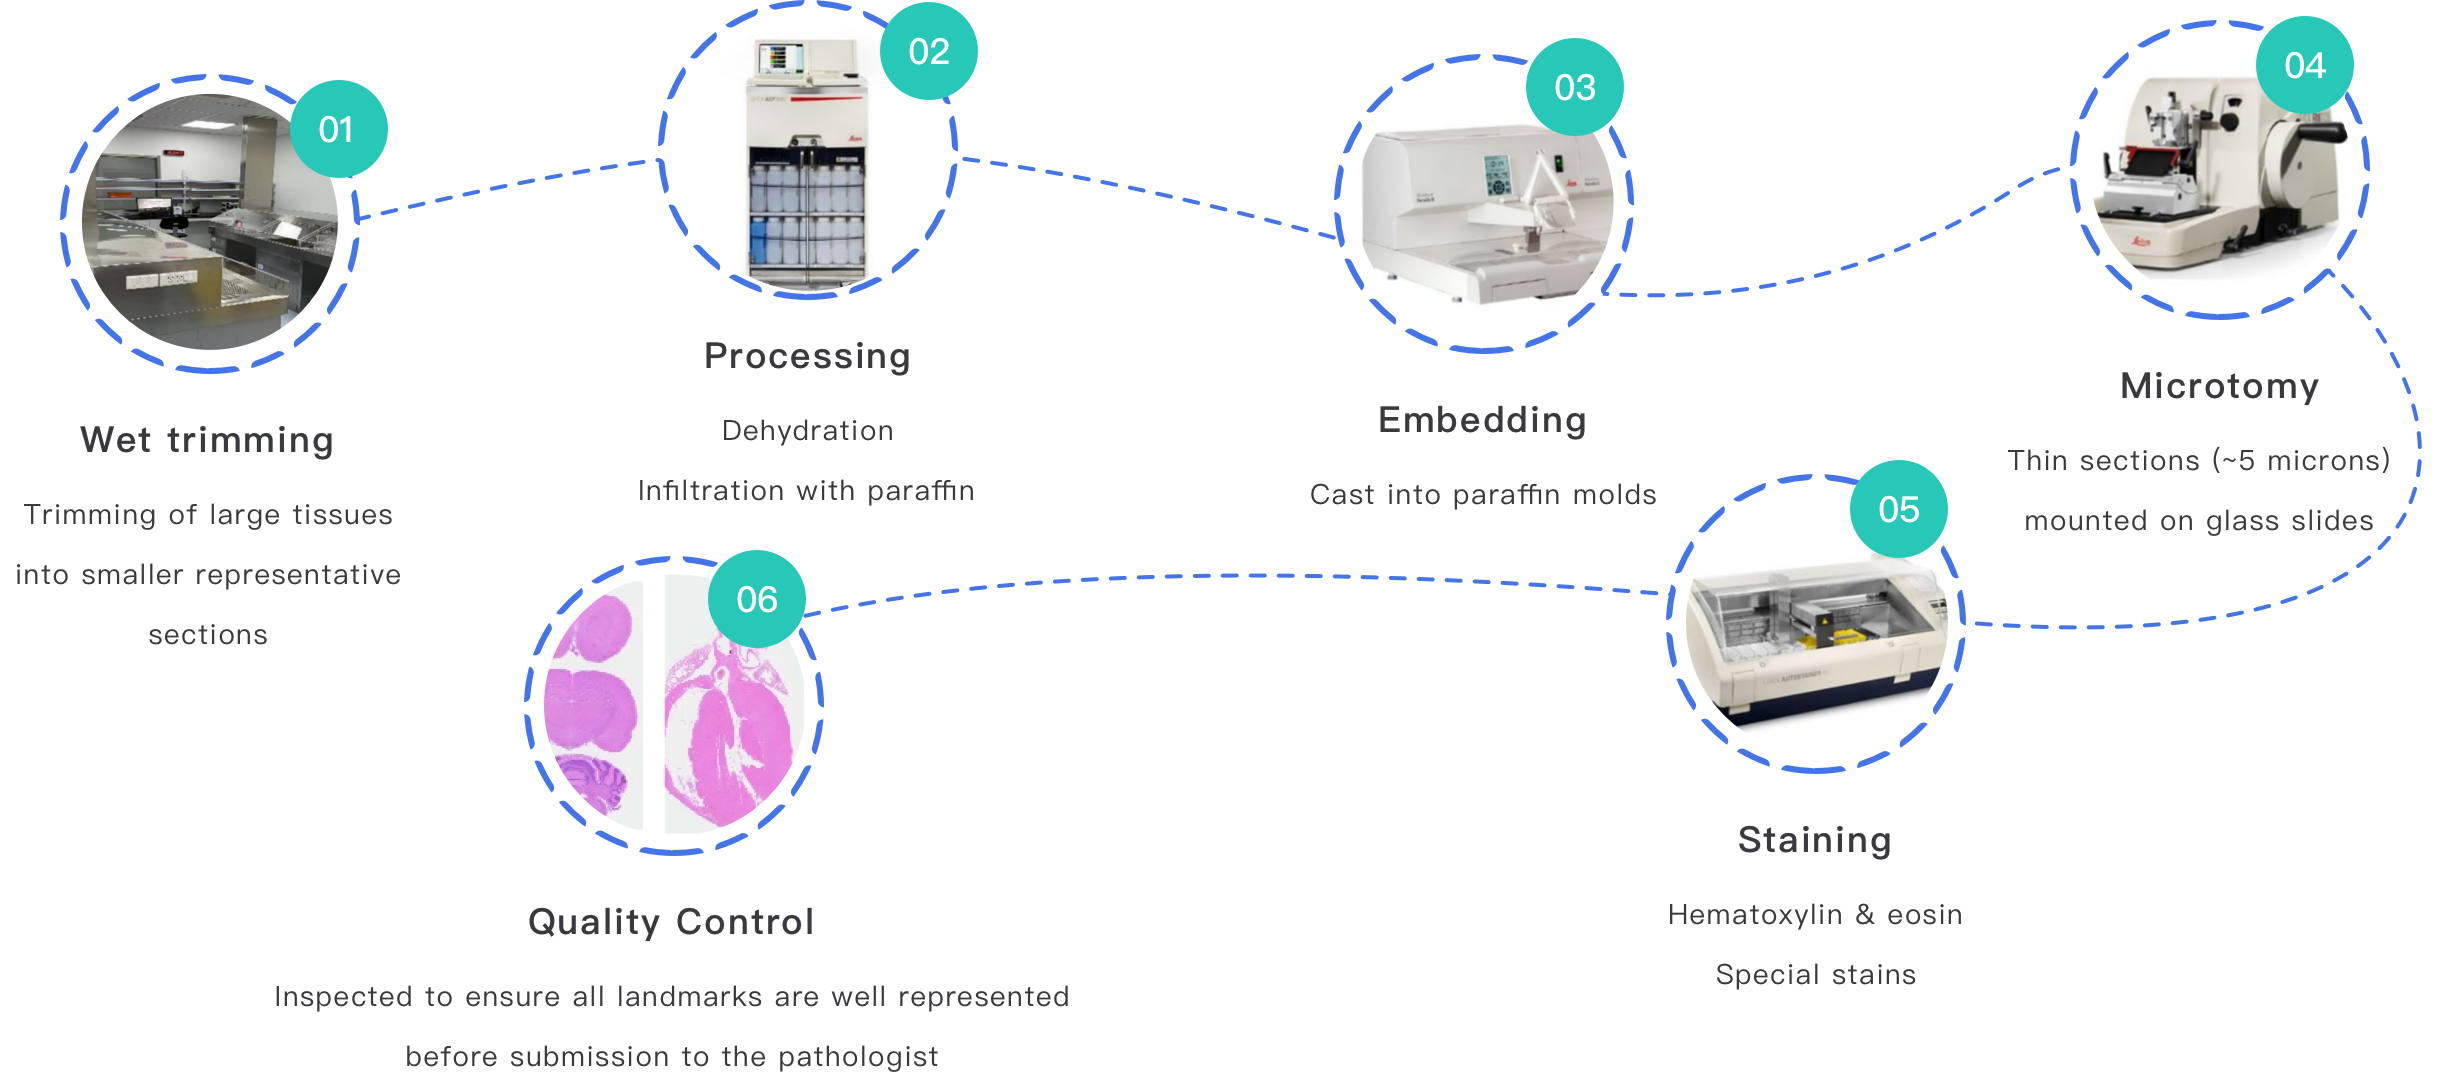
Technically, the root causes are simple: inconsistent fixation, poor paraffin embedding practices, and weak specimen tracking. I remember telling a lab manager, “You have a Leica microtome that can cut 50 blocks a shift, but you have no SOP for cassette labeling.” That mattered. We introduced a single‑page checklist and within three weeks TAT improved by 15%. Look, this was not about buying another instrument; it was about aligning people, SOPs, and stain automation settings. I prefer solutions that start with a thirty‑minute walk through the bench, not a 12‑page procurement brief.
Forward-looking view — case example and practical outlook
When I later consulted for an integrated network (project launched January 2022), we piloted hub‑and‑spoke sample routing between district clinics and an urban hub. The aim: centralized quality control and faster specialist reads. We combined standard preanalytic protocols with a modest upgrade in LIS routing rules and courier schedules. This model — integrated regional laboratories pathology services — cut sample misrouting by 40% and reduced duplicate tests. The tech we used was modest: barcode racks, a Ventana BenchMark Ultra at the hub, and cloud LIS queuing — nothing exotic. The result was predictable: fewer repeats, clearer reports, and clinicians who could act same day instead of waiting three days.
What’s next for teams ready to step up? Start with measured pilots (two referral sites for 90 days), define clear metrics, and protect reagent quality with lot tracking. I like a phased approach: adjust fixation SOPs first, then harmonize stain protocols, then scale autostainer throughput. Little interruptions happen — delays in courier pickup, short staff — and those teach you faster than any slide deck. My sense is that sustainable gains come from small protocol wins rather than wholesale equipment swaps.
Three practical metrics I use to evaluate pathology upgrades
1) Turnaround time stability: measure median and variance for routine biopsies over 30 days. Improvements should lower both median TAT and the spread (standard deviation). In Nairobi I saw variance fall from 24 to 8 hours after simple SOPs were enforced. 2) Preanalytic loss rate: percent of samples rejected for poor fixation, labeling, or transport issues. Aim for single digits; if you’re above 10%, focus there first. 3) Repeat stain rate: percent of slides that require re‑staining due to protocol or reagent errors. Reducing this by even 5% saves reagents and technician hours.
I state these metrics because they relate to real costs — reagent waste, overtime, lost clinical confidence. I’ve used them in procurement meetings and they shift the conversation from glossy brochures to measurable outcomes. For teams planning upgrades, weigh these measures more heavily than headline throughput numbers.
For further verification and device-level testing, see Wuxi AppTec Medical device testing.